What payers will ask
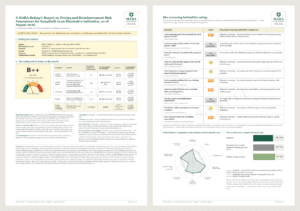
Is the clinical benefit the kind payers reward? — Clinical effectiveness
The evidence for pembrolizumab indicates comparable efficacy to existing chemotherapy options, meeting non-inferiority but lacking direct head-to-head trials. The indirect comparisons suggest that pembrolizumab may lead to longer survival and delayed progression compared to chemotherapy, but these results are uncertain due to the absence of direct evidence.
Does the economic case hold at the expected price? — Cost effectiveness
The cost-effectiveness estimates for pembrolizumab are within NICE’s acceptable range, with ICERs below £30,000 per QALY gained. The economic model considers the severity of the condition and the unmet need for effective treatments, supporting its cost-effectiveness.
Is there quality-of-life evidence payers weigh? — Quality of life
While there are indications of improved quality of life for patients receiving pembrolizumab, the evidence is not robust, and specific HRQoL data from validated instruments are limited. The document does not provide strong evidence of significant improvements in HRQoL compared to standard care.
Does the safety profile hold up for payers? — Safety and Adverse Effects
Pembrolizumab has an acceptable safety profile, with adverse effects primarily being manageable. The document indicates that serious adverse events are rare, and the overall tolerability is good compared to chemotherapy.
Was the drug compared against what payers expect? — Comparator Selection
The document acknowledges that pembrolizumab has not been directly compared with chemotherapy in clinical trials. Instead, it relies on indirect comparisons, which raises concerns about the robustness of the evidence regarding its positioning against standard care.
Is the population defined the way payers need it? — Patient Population and Subgroups
The trials included a diverse patient population across multiple cancer types, and subgroup analyses were conducted. The committee concluded that the trial population is sufficiently representative of the intended real-world patients.
Does the drug fit how care is delivered and paid for? — Care Pathway Integration
Pembrolizumab can be integrated into existing treatment pathways with manageable adjustments, such as the need for routine biomarker testing. The committee noted that the integration would require some planning but is feasible.
Are the wider system costs understood? — Resource Use and Cost Implications
The budget impact of pembrolizumab is considered manageable, with potential net savings due to its effectiveness and the commercial arrangement providing a discount. The overall resource implications are aligned with planning expectations.
Would the evidence survive payer scrutiny? — Evidence Quality and Robustness
The evidence base is primarily derived from phase 2 trials, which introduces limitations in robustness. While the trials provide some insights, the lack of phase 3 data and direct comparisons raises concerns about the overall quality of the evidence.
How exposed is the case to uncertainty? — Uncertainty, Sensitivity, and Broader Impacts
There is considerable uncertainty regarding the treatment effects due to the reliance on indirect comparisons and the small population sizes. However, the context of unmet need and the rarity of the condition provide some mitigating factors.