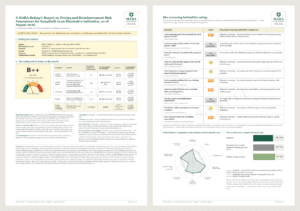
What payers will ask
Is the clinical benefit the kind payers reward? — Clinical effectiveness
The evidence from the PAOLA-1 trial demonstrates a major therapeutic advance, showing a statistically significant improvement in progression-free survival (PFS) and overall survival (OS) for patients receiving olaparib with bevacizumab compared to those receiving bevacizumab alone. The median PFS was 46.8 months for the treatment group versus 17.6 months for the control, and median OS was 75.2 months versus 57.3 months, indicating substantially superior outcomes across key endpoints.
Does the economic case hold at the expected price? — Cost effectiveness
The cost-effectiveness estimates for olaparib with bevacizumab are within acceptable thresholds for Healthcare resources, with the committee concluding that the ICER is below £20,000 per QALY gained when incorporating preferred assumptions. This indicates a clear cost-effective profile under common thresholds.
Is there quality-of-life evidence payers weigh? — Quality of life
The committee noted that the combination treatment offers significant psychological and physical health benefits, improving quality of life for patients with advanced ovarian cancer. The evidence suggests strong quality-of-life gains, particularly in the context of managing anxiety related to cancer recurrence.
Does the safety profile hold up for payers? — Safety and Adverse Effects
The treatment has a very good safety profile, with manageable side effects reported. The committee highlighted that the adverse effects associated with olaparib and bevacizumab are mostly mild to moderate, supporting its tolerability compared to existing therapies.
Was the drug compared against what payers expect? — Comparator Selection
The primary comparator, bevacizumab maintenance treatment, is appropriate as it reflects current clinical practice. The committee concluded that the exclusion of routine surveillance as a comparator was justified, focusing on relevant treatment options.
Is the population defined the way payers need it? — Patient Population and Subgroups
The trial population in PAOLA-1 is broadly representative of the intended patient population, particularly focusing on HRD-positive patients. However, there are some limitations regarding the generalizability due to the trial not including UK participants.
Does the drug fit how care is delivered and paid for? — Care Pathway Integration
The integration of olaparib with bevacizumab into existing care pathways is feasible, requiring only minor adjustments. The treatment aligns well with current clinical practices for managing advanced ovarian cancer.
Are the wider system costs understood? — Resource Use and Cost Implications
The resource implications of implementing olaparib with bevacizumab are manageable, with the potential for net savings due to improved patient outcomes and reduced need for subsequent treatments. The committee noted that the budget impact is aligned with planning.
Would the evidence survive payer scrutiny? — Evidence Quality and Robustness
The evidence base is strong, supported by a Phase 3 RCT (PAOLA-1) with a large sample size and low risk of bias. The committee acknowledged the robustness of the data, although some concerns about the maturity of the data were noted.
How exposed is the case to uncertainty? — Uncertainty, Sensitivity, and Broader Impacts
While there is some uncertainty regarding the long-term survival estimates and the proportion of patients who may achieve a ‘cure’, the overall context is favorable. The committee recognized the importance of addressing unmet needs in this patient population.